


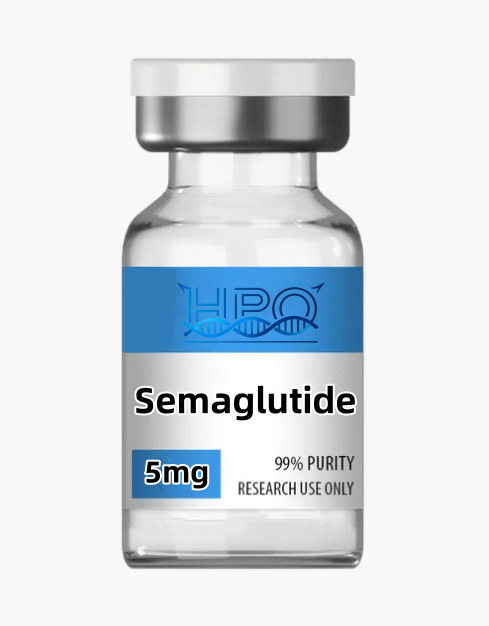
Semaglutide
Price range: $35.00 through $110.00
Semaglutide: Comprehensive Research Guide Semaglutide is a synthetic glucagon-like peptide-1 (GLP-1) receptor agonist that has revolutionized the treatment of type 2 diabetes and obesity. This 31-amin…
DISCLAIMER:
Semaglutide: Comprehensive Research Guide
Semaglutide is a synthetic glucagon-like peptide-1 (GLP-1) receptor agonist that has revolutionized the treatment of type 2 diabetes and obesity. This 31-amino-acid peptide, with a modified amino acid sequence and a fatty acid side chain, was developed to have a prolonged half-life of approximately one week, allowing for once-weekly dosing. Semaglutide has been extensively studied for its effects on blood glucose control, weight loss, cardiovascular health, and various other metabolic parameters. It has become one of the most widely prescribed medications for type 2 diabetes and obesity worldwide, with brand names including Ozempic® (for diabetes) and Wegovy® (for weight management).
At Hanpro Peptides, we provide the highest purity Semaglutide for research purposes only. Our products are manufactured in state-of-the-art facilities and undergo rigorous quality testing to ensure 99%+ purity. This comprehensive guide covers everything researchers need to know about Semaglutide, including its molecular structure, mechanisms of action, research applications, proper handling, and frequently asked questions.
Molecular Structure and Properties
Semaglutide is a 31-amino-acid peptide with the molecular formula C187H291N45O59 and a molecular weight of approximately 4113.6 g/mol. Its amino acid sequence is: H-His-Aib-Glu-Gly-Thr-Phe-Thr-Ser-Asp-Val-Ser-Ser-Tyr-Leu-Glu-Gly-Gln-Ala-Ala-Lys-Glu-Phe-Ile-Ala-Trp-Leu-Val-Arg-Gly-Arg-Gly-OH. The peptide is a modified analog of human GLP-1, with several key modifications that enhance its stability and prolong its half-life.
The key structural modifications of Semaglutide include: (1) Substitution of the 8th amino acid (alanine) with 2-aminoisobutyric acid (Aib), which protects the peptide from degradation by dipeptidyl peptidase-4 (DPP-4); (2) Substitution of the 34th amino acid (lysine) with arginine, which prevents unwanted acylation at this position; (3) Attachment of a C18 fatty acid (stearic acid) side chain to the lysine residue at position 26 via a gamma-glutamic acid spacer and a short polyethylene glycol (PEG) linker. This fatty acid side chain allows Semaglutide to bind to albumin in the bloodstream, which protects it from renal clearance and enzymatic degradation, resulting in a prolonged half-life of approximately 165 hours (about 7 days).
Semaglutide is highly soluble in water and physiological buffers, and it is stable under a wide range of pH and temperature conditions. The peptide’s prolonged half-life and once-weekly dosing regimen make it particularly convenient for both clinical use and research applications. Semaglutide is available in both injectable (subcutaneous) and oral formulations, with the oral formulation requiring co-administration with an absorption enhancer (sodium N-(8-[2-hydroxybenzoyl]amino)caprylate, or SNAC) to improve gastrointestinal absorption.
Mechanisms of Action
Semaglutide exerts its effects through multiple interconnected mechanisms, primarily by acting as a potent and selective agonist of the GLP-1 receptor. Understanding these mechanisms is crucial for designing effective research studies and interpreting results.
1. GLP-1 Receptor Agonism: The primary mechanism of Semaglutide is its ability to bind to and activate the GLP-1 receptor, a G-protein-coupled receptor expressed in various tissues, including pancreatic beta cells, the gastrointestinal tract, the heart, blood vessels, and the central nervous system. Activation of the GLP-1 receptor stimulates adenylate cyclase, increasing intracellular cyclic AMP (cAMP) levels and activating downstream signaling pathways, including protein kinase A (PKA) and exchange protein activated by cAMP (EPAC). These signaling pathways mediate the various physiological effects of Semaglutide, including insulin secretion, glucagon suppression, gastric emptying delay, and appetite regulation.
2. Glucose-Dependent Insulin Secretion: One of the key mechanisms of Semaglutide is its ability to stimulate glucose-dependent insulin secretion from pancreatic beta cells. Unlike traditional insulin secretagogues (such as sulfonylureas), which stimulate insulin secretion regardless of blood glucose levels, Semaglutide only stimulates insulin secretion when blood glucose levels are elevated. This glucose-dependent mechanism significantly reduces the risk of hypoglycemia, a common side effect of many diabetes medications. When blood glucose levels return to normal, the insulin-stimulating effect of Semaglutide diminishes, preventing excessive insulin secretion and hypoglycemia.
3. Glucagon Suppression: Semaglutide also suppresses glucagon secretion from pancreatic alpha cells in a glucose-dependent manner. Glucagon is a hormone that raises blood glucose levels by stimulating hepatic glucose production. By suppressing glucagon secretion, Semaglutide reduces hepatic glucose output, contributing to lower blood glucose levels. Like its effect on insulin secretion, the glucagon-suppressing effect of Semaglutide is glucose-dependent—when blood glucose levels are low, the suppression of glucagon is reduced, preventing excessive hypoglycemia. This dual glucose-dependent effect on insulin and glucagon secretion is one of the key advantages of GLP-1 receptor agonists over traditional diabetes medications.
4. Gastric Emptying Delay: Semaglutide slows the rate of gastric emptying, which reduces the rate at which nutrients (particularly carbohydrates) are absorbed from the gastrointestinal tract into the bloodstream. This delayed gastric emptying contributes to lower postprandial (after-meal) blood glucose spikes and helps regulate overall glycemic control. The gastric emptying delay also contributes to the weight loss effects of Semaglutide, as it increases feelings of fullness and satiety, reducing overall food intake. However, the gastric emptying effect of Semaglutide may diminish over time with chronic use, a phenomenon known as tachyphylaxis, which may explain why the weight loss effects of Semaglutide tend to plateau after several months of use.
5. Appetite Regulation and Central Nervous System Effects: Semaglutide exerts significant effects on appetite and food intake through its actions on the central nervous system. The GLP-1 receptor is expressed in various regions of the brain involved in appetite regulation, including the hypothalamus, the brainstem, and the reward centers. Semaglutide can cross the blood-brain barrier and directly activate GLP-1 receptors in these brain regions, reducing appetite, increasing feelings of satiety, and reducing the rewarding effects of food. The peptide also reduces cravings for high-calorie, high-fat foods and reduces overall food intake. These central nervous system effects are the primary mechanism by which Semaglutide promotes weight loss, and they contribute to its efficacy in treating obesity and metabolic syndrome.
6. Cardiovascular Protective Effects: Semaglutide has demonstrated significant cardiovascular protective effects in large-scale clinical trials, reducing the risk of major adverse cardiovascular events (MACE) in patients with type 2 diabetes and established cardiovascular disease. The cardiovascular protective effects of Semaglutide are mediated through multiple mechanisms, including: (1) Reduction of blood glucose levels and glycated hemoglobin (HbA1c), reducing the cardiovascular damage caused by chronic hyperglycemia; (2) Reduction of body weight and visceral adiposity, reducing cardiovascular risk factors; (3) Reduction of blood pressure, particularly systolic blood pressure; (4) Improvement of lipid profiles, including reduction of triglycerides and LDL cholesterol, and increase of HDL cholesterol; (5) Reduction of inflammation markers, including C-reactive protein (CRP); (6) Direct protective effects on the vascular endothelium and the heart muscle, mediated through GLP-1 receptor activation in these tissues. The cardiovascular protective effects of Semaglutide have been confirmed in large-scale clinical trials, including the SUSTAIN-6 trial, which showed that Semaglutide reduced the risk of MACE by 26% in patients with type 2 diabetes and high cardiovascular risk.
7. Renal Protective Effects: Semaglutide has also demonstrated renal protective effects in clinical trials, reducing the risk of kidney disease progression in patients with type 2 diabetes. The renal protective effects of Semaglutide are mediated through multiple mechanisms, including: (1) Reduction of blood glucose levels and HbA1c, reducing the renal damage caused by chronic hyperglycemia; (2) Reduction of blood pressure, particularly systolic blood pressure, reducing intraglomerular pressure and renal damage; (3) Reduction of body weight and visceral adiposity, reducing renal risk factors; (4) Reduction of inflammation markers, reducing renal inflammation; (5) Direct protective effects on renal cells, mediated through GLP-1 receptor activation in the kidneys. The renal protective effects of Semaglutide have been confirmed in the SUSTAIN-6 trial, which showed that Semaglutide reduced the risk of new or worsening nephropathy by 36% in patients with type 2 diabetes and high cardiovascular risk.
Research Applications
Semaglutide has been investigated in numerous preclinical and clinical studies for its potential therapeutic applications across various medical fields. The following sections highlight the most important areas of research.
1. Type 2 Diabetes Mellitus
The primary and most well-established application of Semaglutide is in the treatment of type 2 diabetes mellitus. Semaglutide has been extensively studied in the SUSTAIN (Semaglutide Unabated Sustainability in Treatment of Type 2 Diabetes) clinical trial program, which included over 10,000 patients with type 2 diabetes across multiple phases and treatment regimens.
The SUSTAIN trials demonstrated that Semaglutide, administered once weekly via subcutaneous injection, produced significant and sustained reductions in HbA1c (glycated hemoglobin) levels, with mean reductions ranging from 1.0% to 1.8% depending on the dose and patient population. Semaglutide was shown to be superior to several other diabetes medications, including sitagliptin (a DPP-4 inhibitor), exenatide extended-release (another GLP-1 receptor agonist), insulin glargine (a long-acting insulin), and dulaglutide (another once-weekly GLP-1 receptor agonist), in terms of HbA1c reduction.
In addition to reducing HbA1c levels, Semaglutide also produced significant reductions in fasting plasma glucose and postprandial glucose levels, improving overall glycemic control. The glucose-dependent mechanism of action of Semaglutide resulted in a low risk of hypoglycemia, particularly when used as monotherapy or in combination with non-hypoglycemia-inducing medications. When used in combination with insulin or sulfonylureas, the risk of hypoglycemia was higher, but still lower than with many other diabetes medications.
Semaglutide also produced significant weight loss in patients with type 2 diabetes, with mean weight reductions ranging from 3 kg to 6 kg depending on the dose and treatment duration. This weight loss effect is particularly beneficial for patients with type 2 diabetes, many of whom are overweight or obese, and weight loss can improve insulin sensitivity and overall metabolic health.
The safety and tolerability of Semaglutide were generally good in the SUSTAIN trials, with the most common adverse events being gastrointestinal in nature, including nausea, vomiting, diarrhea, constipation, and abdominal pain. These gastrointestinal side effects were generally mild to moderate in severity, occurred primarily during the first few weeks of treatment, and tended to diminish over time as patients developed tolerance. The incidence of gastrointestinal side effects was dose-dependent, with higher doses associated with a higher incidence of side effects. To minimize gastrointestinal side effects, Semaglutide is typically initiated at a low dose and gradually titrated up to the target dose over several weeks.
Semaglutide has also been studied in special populations, including elderly patients, patients with renal impairment, patients with hepatic impairment, and patients with cardiovascular disease. The results of these studies showed that Semaglutide was generally safe and effective in these special populations, with no dose adjustments required for age, renal impairment, or hepatic impairment (with the exception of severe renal impairment, where caution is advised). The cardiovascular safety of Semaglutide was confirmed in the SUSTAIN-6 trial, which showed that Semaglutide reduced the risk of major adverse cardiovascular events in patients with type 2 diabetes and high cardiovascular risk.
2. Obesity and Weight Management
One of the most significant and widely studied applications of Semaglutide is in the treatment of obesity and weight management. The weight loss effects of Semaglutide were first observed in the SUSTAIN trials for type 2 diabetes, where patients treated with Semaglutide experienced significant weight loss. This led to the development of a higher-dose formulation of Semaglutide (2.4 mg once weekly) specifically for the treatment of obesity, marketed under the brand name Wegovy®.
The efficacy of Semaglutide for weight management has been extensively studied in the STEP (Semaglutide Treatment Effect in People with obesity) clinical trial program, which included over 10,000 patients with obesity or overweight across multiple phases and treatment regimens.
The STEP trials demonstrated that Semaglutide 2.4 mg once weekly, in combination with lifestyle intervention (reduced-calorie diet and increased physical activity), produced significant and sustained weight loss in patients with obesity or overweight. In the STEP 1 trial, which included patients with obesity or overweight without diabetes, treatment with Semaglutide 2.4 mg once weekly for 68 weeks resulted in a mean weight reduction of 14.9% from baseline, compared to 2.4% with placebo. Approximately one-third of patients treated with Semaglutide achieved weight loss of 20% or more from baseline, and over 85% of patients achieved weight loss of 5% or more.
The STEP 2 trial, which included patients with obesity and type 2 diabetes, showed that Semaglutide 2.4 mg once weekly for 68 weeks resulted in a mean weight reduction of 9.6% from baseline, compared to 3.4% with placebo. The weight loss in patients with type 2 diabetes was somewhat less than in patients without diabetes, but still clinically significant. The STEP 3 trial, which included intensive behavioral therapy in addition to Semaglutide, showed even greater weight loss, with a mean reduction of 16.0% from baseline at 68 weeks. The STEP 4 trial, which evaluated the maintenance of weight loss after initial treatment, showed that continued treatment with Semaglutide was necessary to maintain weight loss, as patients who switched to placebo experienced significant weight regain.
In addition to weight loss, Semaglutide also produced significant improvements in various cardiometabolic risk factors in patients with obesity, including: (1) Reduction of blood pressure, particularly systolic blood pressure; (2) Improvement of lipid profiles, including reduction of triglycerides and LDL cholesterol, and increase of HDL cholesterol; (3) Reduction of inflammation markers, including C-reactive protein (CRP); (4) Improvement of glycemic control, including reduction of fasting glucose and HbA1c levels; (5) Reduction of waist circumference and visceral adiposity; (6) Improvement of insulin sensitivity and beta-cell function. These improvements in cardiometabolic risk factors are likely to translate into long-term reductions in cardiovascular morbidity and mortality, although long-term cardiovascular outcomes trials for Semaglutide in obesity are still ongoing.
The safety and tolerability of Semaglutide for weight management were generally good in the STEP trials, with the most common adverse events being gastrointestinal in nature, including nausea, diarrhea, vomiting, constipation, and abdominal pain. These gastrointestinal side effects were generally mild to moderate in severity, occurred primarily during the dose-titration phase, and tended to diminish over time. The incidence of gallbladder-related events (including gallstones and cholecystitis) was slightly higher in patients treated with Semaglutide compared to placebo, which is consistent with the known increased risk of gallbladder disease with rapid weight loss. The incidence of pancreatitis was low and similar between Semaglutide and placebo groups, although a small increased risk cannot be ruled out. As with the diabetes formulation, Semaglutide for weight management is initiated at a low dose and gradually titrated up to the target dose over several months to minimize gastrointestinal side effects.
Semaglutide has also been studied in special populations for weight management, including elderly patients, patients with type 2 diabetes, patients with prediabetes, patients with obstructive sleep apnea, and patients with non-alcoholic steatohepatitis (NASH). The results of these studies showed that Semaglutide was generally safe and effective for weight loss in these special populations, with additional benefits in terms of improved glycemic control, reduced sleep apnea severity, and improved liver health. The STEP 6 trial, which evaluated the efficacy of Semaglutide in adolescents with obesity, showed that Semaglutide produced significant weight loss in adolescents, with a mean reduction of 16.1% in BMI from baseline at 68 weeks, compared to 0.2% with placebo.
3. Cardiovascular Disease Protection
Semaglutide has demonstrated significant cardiovascular protective effects in large-scale clinical trials, making it one of the few diabetes medications with proven cardiovascular benefit. The cardiovascular safety and efficacy of Semaglutide were first established in the SUSTAIN-6 trial, a randomized, double-blind, placebo-controlled trial that included 3,297 patients with type 2 diabetes and high cardiovascular risk. The results of SUSTAIN-6 showed that treatment with Semaglutide (0.5 mg or 1.0 mg once weekly) for a median of 2.1 years reduced the risk of major adverse cardiovascular events (MACE, defined as cardiovascular death, non-fatal myocardial infarction, or non-fatal stroke) by 26% compared to placebo. The reduction in MACE was driven primarily by a reduction in non-fatal stroke, with a 39% reduction in stroke risk observed in the Semaglutide group compared to placebo.
In addition to reducing MACE, Semaglutide also reduced the risk of other cardiovascular outcomes in the SUSTAIN-6 trial, including: (1) Reduction of new or worsening nephropathy by 36%; (2) Reduction of all-cause mortality by 18% (not statistically significant); (3) Reduction of cardiovascular death by 22% (not statistically significant); (4) Reduction of heart failure hospitalization by 9% (not statistically significant). The cardiovascular protective effects of Semaglutide were consistent across various subgroups, including age, sex, race, baseline HbA1c, baseline BMI, duration of diabetes, and history of cardiovascular disease.
The cardiovascular protective effects of Semaglutide are mediated through multiple mechanisms, including: (1) Reduction of blood glucose levels and HbA1c, reducing the cardiovascular damage caused by chronic hyperglycemia; (2) Reduction of body weight and visceral adiposity, reducing cardiovascular risk factors; (3) Reduction of blood pressure, particularly systolic blood pressure; (4) Improvement of lipid profiles, including reduction of triglycerides and LDL cholesterol, and increase of HDL cholesterol; (5) Reduction of inflammation markers, including C-reactive protein (CRP); (6) Improvement of endothelial function and vascular health; (7) Direct protective effects on the heart muscle, mediated through GLP-1 receptor activation in cardiac cells; (8) Reduction of oxidative stress and advanced glycation end products (AGEs).
The cardiovascular protective effects of Semaglutide have led to its inclusion in major clinical practice guidelines for the management of type 2 diabetes. The American Diabetes Association (ADA) and the European Association for the Study of Diabetes (EASD) now recommend GLP-1 receptor agonists with proven cardiovascular benefit (including Semaglutide) as first-line or second-line therapy for patients with type 2 diabetes and established cardiovascular disease or high cardiovascular risk, regardless of baseline HbA1c levels. This recommendation represents a paradigm shift in the management of type 2 diabetes, from a glucose-centric approach to a more holistic approach that prioritizes cardiovascular and renal protection.
Long-term cardiovascular outcomes trials for Semaglutide in patients without diabetes (the SELECT trial) are currently ongoing. The SELECT trial is a randomized, double-blind, placebo-controlled trial that includes approximately 17,600 patients with established cardiovascular disease and overweight or obesity, without diabetes. The primary endpoint of the SELECT trial is MACE, and the trial is expected to complete in 2023. The results of the SELECT trial will provide important information about the cardiovascular protective effects of Semaglutide in patients without diabetes, and may lead to expanded indications for Semaglutide in the prevention of cardiovascular disease in patients with obesity.
4. Non-Alcoholic Fatty Liver Disease (NAFLD) and Non-Alcoholic Steatohepatitis (NASH)
Non-alcoholic fatty liver disease (NAFLD) and its more severe form, non-alcoholic steatohepatitis (NASH), are increasingly common liver diseases characterized by the accumulation of fat in the liver, inflammation, and liver damage. NASH can progress to liver fibrosis, cirrhosis, liver failure, and hepatocellular carcinoma, and it is currently one of the leading causes of liver transplantation worldwide. There are currently no FDA-approved medications for the treatment of NASH, and there is a significant unmet medical need for effective therapies.
Semaglutide has been investigated as a potential treatment for NASH, based on its ability to reduce body weight, improve insulin sensitivity, reduce inflammation, and improve liver health. The efficacy of Semaglutide for NASH has been studied in several preclinical and clinical trials, with promising results.
In a phase 2 clinical trial, 320 patients with biopsy-confirmed NASH and liver fibrosis (stage F1-F3) were randomized to receive Semaglutide 0.1 mg, 0.2 mg, or 0.4 mg once daily, or placebo, for 72 weeks. The results of this trial showed that treatment with Semaglutide 0.4 mg once daily resulted in a significantly higher rate of NASH resolution (defined as improvement in steatosis, inflammation, and hepatocellular ballooning, without worsening of fibrosis) compared to placebo (59% vs. 17%, p<0.001). Treatment with Semaglutide also resulted in a significantly higher rate of improvement in liver fibrosis (defined as improvement of at least one stage of fibrosis, without worsening of NASH) compared to placebo (43% vs. 19%, p=0.001 for the 0.4 mg dose).
In addition to NASH resolution and fibrosis improvement, Semaglutide also produced significant improvements in various liver-related and metabolic parameters in patients with NASH, including: (1) Reduction of liver fat content, as measured by MRI-PDFF; (2) Reduction of liver enzymes, including ALT and AST; (3) Reduction of body weight and visceral adiposity; (4) Improvement of glycemic control, including reduction of fasting glucose and HbA1c levels; (5) Improvement of insulin sensitivity; (6) Reduction of inflammation markers, including CRP; (7) Improvement of lipid profiles. These improvements in liver health and metabolic parameters are likely to translate into long-term reductions in liver-related morbidity and mortality, although long-term outcomes trials for Semaglutide in NASH are still ongoing.
The safety and tolerability of Semaglutide in patients with NASH were generally good, with the most common adverse events being gastrointestinal in nature, including nausea, diarrhea, vomiting, constipation, and abdominal pain. These gastrointestinal side effects were generally mild to moderate in severity and tended to diminish over time. The incidence of serious adverse events was similar between Semaglutide and placebo groups, and there were no cases of pancreatitis or gallbladder-related events in the Semaglutide groups. Based on these promising phase 2 results, Semaglutide is currently being evaluated in phase 3 clinical trials for the treatment of NASH, with the first phase 3 trial (ESSENCE) expected to complete in 2024.
5. Other Research Applications
In addition to the well-established applications in type 2 diabetes, obesity, cardiovascular disease, and NASH, Semaglutide has been investigated in several other research areas, with promising preliminary results.
Alzheimer’s Disease and Cognitive Decline: Semaglutide has been investigated as a potential treatment for Alzheimer’s disease and cognitive decline, based on its neuroprotective effects, anti-inflammatory properties, and ability to improve insulin sensitivity in the brain. The EVOKE and EVOKE Plus phase 3 clinical trials are currently evaluating the efficacy of Semaglutide for the treatment of early Alzheimer’s disease, with results expected in 2025. Preliminary results from preclinical studies and smaller clinical trials have shown that Semaglutide may reduce neuroinflammation, improve synaptic function, and reduce amyloid-beta plaque formation in animal models of Alzheimer’s disease.
Polycystic Ovary Syndrome (PCOS): Semaglutide has been investigated as a potential treatment for polycystic ovary syndrome (PCOS), a common endocrine disorder characterized by insulin resistance, hyperandrogenism, and ovarian dysfunction. In small clinical trials, treatment with Semaglutide resulted in significant weight loss, improvement in insulin sensitivity, reduction of androgen levels, and improvement in menstrual regularity in women with PCOS. Larger clinical trials are needed to confirm these results and to evaluate the long-term safety and efficacy of Semaglutide in PCOS.
Obstructive Sleep Apnea (OSA): Semaglutide has been investigated as a potential treatment for obstructive sleep apnea, based on its ability to reduce body weight and improve metabolic health. In the STEP 2 trial, which included patients with obesity and type 2 diabetes, treatment with Semaglutide resulted in a significant reduction in the severity of obstructive sleep apnea, as measured by the apnea-hypopnea index (AHI). Larger clinical trials specifically evaluating the efficacy of Semaglutide for OSA are ongoing.
Addiction and Substance Use Disorders: Semaglutide has been investigated as a potential treatment for addiction and substance use disorders, based on its effects on the brain’s reward system and its ability to reduce cravings for food. Preliminary preclinical studies and small clinical trials have shown that Semaglutide may reduce cravings for alcohol, nicotine, and various drugs of abuse, and may reduce substance use in individuals with addiction disorders. Larger clinical trials are needed to confirm these results and to evaluate the safety and efficacy of Semaglutide in addiction treatment.
Inflammatory Bowel Disease (IBD): Semaglutide has been investigated as a potential treatment for inflammatory bowel disease (IBD), including Crohn’s disease and ulcerative colitis, based on its anti-inflammatory properties and its ability to promote intestinal healing. In preclinical studies, treatment with Semaglutide reduced intestinal inflammation, preserved mucosal integrity, and improved clinical symptoms in animal models of IBD. Small clinical trials in humans have also shown promising results, with Semaglutide reducing disease activity and improving quality of life in patients with IBD. Larger clinical trials are needed to confirm these results.
Product Specifications
| Product Name | Semaglutide |
| Full Name | Semaglutide (GLP-1 Receptor Agonist) |
| Sequence | H-His-Aib-Glu-Gly-Thr-Phe-Thr-Ser-Asp-Val-Ser-Ser-Tyr-Leu-Glu-Gly-Gln-Ala-Ala-Lys(γ-Glu-PEG-C18 fatty acid)-Glu-Phe-Ile-Ala-Trp-Leu-Val-Arg-Gly-Arg-Gly-OH |
| Molecular Formula | C187H291N45O59 |
| Molecular Weight | 4113.6 g/mol |
| Purity | ≥99% |
| Appearance | White lyophilized powder |
| Solubility | Soluble in water (1 mg/mL) and physiological buffers |
| Storage | Store at -20°C upon receipt. After reconstitution, store at 2-8°C for up to 30 days. |
| Available Sizes | 5mg, 10mg, 15mg, 30mg |
| Quality Control | HPLC, Mass Spectrometry, COA provided |
Reconstitution and Handling Guidelines
Proper reconstitution and handling are essential for maintaining the stability and efficacy of Semaglutide. Follow these guidelines carefully to ensure optimal results in your research.
Reconstitution Procedure:
- Allow the vial to reach room temperature before opening (approximately 15-20 minutes).
- Wipe the rubber stopper with an alcohol swab and allow it to dry.
- Using a sterile syringe, inject the appropriate volume of bacteriostatic water or sterile saline into the vial. For a 5mg vial, add 2.5mL of solvent to achieve a concentration of 2mg/mL. For a 10mg vial, add 5mL of solvent for a 2mg/mL concentration.
- Gently swirl the vial until the powder is completely dissolved. Do not shake vigorously, as this can denature the peptide. The solution should be clear and colorless.
- Once fully dissolved, inspect the solution for any particles or discoloration. If you notice any particles or significant discoloration, do not use the solution.
Storage After Reconstitution:
- Store reconstituted Semaglutide in a refrigerator at 2-8°C (36-46°F).
- When stored properly, reconstituted Semaglutide remains stable for up to 30 days.
- For long-term storage (up to 6 months), aliquot the solution into individual doses and store at -20°C. Avoid repeated freeze-thaw cycles, as this can degrade the peptide.
- Do not store reconstituted peptide in direct sunlight or at room temperature for extended periods.
Handling Precautions:
- Always wear gloves and use sterile technique when handling Semaglutide.
- Use only sterile syringes and needles for reconstitution and administration.
- Do not mix Semaglutide with other peptides or compounds in the same vial unless you have verified compatibility and stability.
- If you are using Semaglutide for in vitro studies, dilute it to the desired concentration using appropriate buffer solutions.
- Semaglutide should be administered via subcutaneous injection for in vivo studies. Rotate injection sites to minimize local reactions.
Frequently Asked Questions (FAQ)
Q1: What is Semaglutide and how does it work?
A: Semaglutide is a synthetic glucagon-like peptide-1 (GLP-1) receptor agonist, which means it mimics the action of the naturally occurring hormone GLP-1. GLP-1 is a hormone released by the intestines in response to food intake, and it plays a key role in regulating blood glucose levels, appetite, and gastric emptying. Semaglutide works by binding to and activating the GLP-1 receptor, which is expressed in various tissues, including the pancreas, gastrointestinal tract, heart, blood vessels, and brain. Activation of the GLP-1 receptor stimulates glucose-dependent insulin secretion from pancreatic beta cells, suppresses glucagon secretion from pancreatic alpha cells, slows gastric emptying, reduces appetite and food intake, and exerts cardiovascular and renal protective effects. Semaglutide has been modified to have a prolonged half-life of approximately one week, allowing for once-weekly dosing, which makes it more convenient for both clinical use and research applications. Semaglutide is available under the brand names Ozempic® (for type 2 diabetes) and Wegovy® (for weight management), and it is also available in an oral formulation (Rybelsus®) for type 2 diabetes.
Q2: Is Semaglutide legal for research purposes?
A: Yes, Semaglutide is legal for research purposes in most countries, including the United States, when purchased from reputable suppliers and used strictly for laboratory research. Semaglutide is an FDA-approved medication for the treatment of type 2 diabetes and obesity, but it is a prescription medication that should only be used under the supervision of a qualified healthcare provider for clinical purposes. For research purposes, Semaglutide can be purchased from reputable peptide suppliers and used in preclinical and clinical research studies in accordance with applicable regulations and institutional guidelines. Researchers must ensure that their use of Semaglutide complies with all applicable local, state, and federal regulations, as well as institutional review board (IRB) guidelines for human subjects research and institutional animal care and use committee (IACUC) guidelines for animal research. At Hanpro Peptides, we sell Semaglutide exclusively for research purposes, and all purchasers must agree to use the product only for legitimate scientific research. It is important to note that Semaglutide is a controlled substance in some countries, and researchers should verify the legal status of Semaglutide in their jurisdiction before purchasing or using it for research purposes.
Q3: What is the recommended dosage for Semaglutide in research studies?
A: The optimal dosage of Semaglutide varies depending on the specific research application, animal model, and route of administration. In preclinical animal studies, dosages have ranged from 0.005 mg/kg to 1 mg/kg body weight per day, depending on the species and study design. For rodent studies, typical dosages range from 0.01 mg/kg to 0.3 mg/kg per day, administered via subcutaneous injection. For larger animal models (such as non-human primates), dosages are typically lower, ranging from 0.005 mg/kg to 0.1 mg/kg per day. For in vitro studies, concentrations typically range from 1 nM to 10 μM, with most studies using concentrations between 10 nM and 1 μM. It is important to note that these are research dosages and should not be interpreted as recommendations for human use. In clinical studies, Semaglutide is typically initiated at a low dose (0.25 mg once weekly for diabetes, or 0.25 mg once weekly for weight management) and gradually titrated up to the target dose (0.5 mg or 1.0 mg once weekly for diabetes, or 2.4 mg once weekly for weight management) over several weeks to minimize gastrointestinal side effects. Researchers should consult published literature and conduct dose-response studies to determine the optimal dosage for their specific research application. Always follow institutional guidelines and ethical protocols when conducting research with peptides.
Q4: What are the most common side effects of Semaglutide?
A: The most common side effects of Semaglutide are gastrointestinal in nature, including nausea, vomiting, diarrhea, constipation, and abdominal pain. These gastrointestinal side effects occur in approximately 20-40% of patients, are generally mild to moderate in severity, occur primarily during the first few weeks of treatment (particularly during dose titration), and tend to diminish over time as patients develop tolerance. The incidence of gastrointestinal side effects is dose-dependent, with higher doses associated with a higher incidence of side effects. To minimize gastrointestinal side effects, Semaglutide is typically initiated at a low dose and gradually titrated up to the target dose over several weeks. Other common side effects include: (1) Injection site reactions, including redness, swelling, itching, or pain at the injection site (occurring in approximately 5-10% of patients); (2) Headache (occurring in approximately 5-10% of patients); (3) Fatigue or tiredness (occurring in approximately 5-10% of patients); (4) Dizziness (occurring in approximately 3-5% of patients); (5) Dyspepsia or indigestion (occurring in approximately 5-10% of patients); (6) Gastritis or gastroesophageal reflux disease (GERD) (occurring in approximately 3-5% of patients). Serious but rare side effects include: (1) Pancreatitis (inflammation of the pancreas), occurring in approximately 0.1-0.5% of patients; (2) Gallbladder disease, including gallstones and cholecystitis, occurring in approximately 1-3% of patients (particularly with rapid weight loss); (3) Hypoglycemia (low blood sugar), particularly when used in combination with insulin or sulfonylureas; (4) Allergic reactions, including rash, itching, and angioedema; (5) Diabetic retinopathy complications (in patients with pre-existing diabetic retinopathy); (6) Acute kidney injury, particularly in patients with dehydration from gastrointestinal side effects. It is important to note that Semaglutide has a black box warning for thyroid C-cell tumors, based on findings in animal studies. However, the clinical significance of this finding in humans is unclear, and no cases of thyroid C-cell tumors have been definitively linked to Semaglutide use in humans. Patients with a personal or family history of medullary thyroid carcinoma (MTC) or multiple endocrine neoplasia syndrome type 2 (MEN 2) should not use Semaglutide. Researchers should always follow proper safety protocols and consult institutional safety guidelines when working with Semaglutide.
Q5: How does Semaglutide compare to other GLP-1 receptor agonists?
A: Semaglutide is one of several GLP-1 receptor agonists currently available for clinical use and research, and it has several unique characteristics that distinguish it from other GLP-1 receptor agonists. Compared to other GLP-1 receptor agonists: (1) vs. Liraglutide (Victoza®, Saxenda®): Liraglutide is a once-daily GLP-1 receptor agonist with a half-life of approximately 13 hours. Semaglutide has a longer half-life (approximately 165 hours), allowing for once-weekly dosing, which is more convenient for patients and may improve adherence. In head-to-head clinical trials (SUSTAIN-10), Semaglutide 1.0 mg once weekly produced significantly greater reductions in HbA1c and body weight compared to liraglutide 1.8 mg once daily. (2) vs. Dulaglutide (Trulicity®): Dulaglutide is a once-weekly GLP-1 receptor agonist with a half-life of approximately 5 days. In head-to-head clinical trials (SUSTAIN-7), Semaglutide 1.0 mg once weekly produced significantly greater reductions in HbA1c and body weight compared to dulaglutide 1.5 mg once weekly. (3) vs. Exenatide extended-release (Bydureon®): Exenatide extended-release is a once-weekly GLP-1 receptor agonist with a half-life of approximately 2-3 days. In head-to-head clinical trials (SUSTAIN-3), Semaglutide 1.0 mg once weekly produced significantly greater reductions in HbA1c and body weight compared to exenatide extended-release 2.0 mg once weekly. (4) vs. Tirzepatide (Mounjaro®): Tirzepatide is a dual GLP-1 and GIP (glucose-dependent insulinotropic polypeptide) receptor agonist, which is a newer class of medications. In head-to-head clinical trials (SURPASS-2), tirzepatide produced significantly greater reductions in HbA1c and body weight compared to Semaglutide, particularly at higher doses. However, tirzepatide is a newer medication with less long-term safety data compared to Semaglutide. (5) vs. Oral Semaglutide (Rybelsus®): Oral Semaglutide is an oral formulation of Semaglutide that is co-administered with an absorption enhancer (SNAC) to improve gastrointestinal absorption. Oral Semaglutide is taken once daily, and it produces similar reductions in HbA1c and body weight compared to injectable Semaglutide, although it may have slightly lower bioavailability. In summary, Semaglutide is one of the most potent and widely prescribed GLP-1 receptor agonists, with proven efficacy for glycemic control, weight loss, and cardiovascular protection, and a convenient once-weekly dosing regimen. At Hanpro Peptides, we offer a wide range of GLP-1 receptor agonists for research purposes, including Semaglutide, Liraglutide, Dulaglutide, Exenatide, Tirzepatide, and many others.
Q6: Can Semaglutide be used in combination with other peptides or medications?
A: Yes, Semaglutide can be used in combination with other peptides or medications for research purposes, and combination therapy is an active area of research. However, researchers should carefully consider the potential interactions, additive effects, and safety of combination therapy before using Semaglutide in combination with other peptides or medications. Common combination therapies being investigated include: (1) Semaglutide + Insulin: Semaglutide is frequently used in combination with basal insulin (such as insulin glargine or insulin degludec) for the treatment of type 2 diabetes. The combination of Semaglutide and insulin produces greater reductions in HbA1c compared to either medication alone, with a lower risk of hypoglycemia and less weight gain compared to insulin alone. However, the risk of hypoglycemia is higher with combination therapy, and insulin doses may need to be adjusted. (2) Semaglutide + Metformin: Semaglutide is frequently used in combination with metformin, a first-line medication for type 2 diabetes. The combination of Semaglutide and metformin produces greater reductions in HbA1c and body weight compared to either medication alone, with a low risk of hypoglycemia. This combination is generally well-tolerated and is a common treatment regimen for type 2 diabetes. (3) Semaglutide + SGLT2 Inhibitors: Semaglutide is frequently used in combination with SGLT2 inhibitors (such as empagliflozin, dapagliflozin, or canagliflozin) for the treatment of type 2 diabetes, particularly in patients with cardiovascular or renal disease. The combination of Semaglutide and SGLT2 inhibitors produces greater reductions in HbA1c, body weight, and blood pressure compared to either medication alone, and the combination may have additive cardiovascular and renal protective effects. (4) Semaglutide + Growth Hormone Secretagogues: Semaglutide is sometimes used in combination with growth hormone secretagogues (such as Ipamorelin, CJC-1295, or Tesamorelin) for research purposes, particularly in studies investigating body composition, muscle mass, and metabolic health. The combination of Semaglutide (which promotes fat loss) and growth hormone secretagogues (which promote muscle growth and fat loss) may have synergistic effects on body composition. However, researchers should carefully monitor glucose levels, as growth hormone can increase blood glucose levels and may counteract the glucose-lowering effects of Semaglutide. (5) Semaglutide + Other Peptides: Semaglutide can also be used in combination with other peptides for various research applications, including BPC-157, TB-500, GHK-Cu, and others. However, researchers should carefully consider the potential interactions and safety of these combinations, as there is limited research on the safety and efficacy of combining Semaglutide with other peptides. It is important to note that combination therapy may increase the risk of side effects, particularly gastrointestinal side effects, hypoglycemia, and other metabolic effects. Researchers should always consult published literature and conduct appropriate safety studies before using Semaglutide in combination with other peptides or medications. Always follow institutional guidelines and ethical protocols when conducting research with peptides.
Q7: What is the shelf life of Semaglutide, and how should it be stored?
A: When stored properly, lyophilized (freeze-dried) Semaglutide has a shelf life of up to 2 years from the date of manufacture when stored at -20°C in a freezer. It is important to keep the peptide in its original sealed vial and protect it from light, moisture, and temperature fluctuations. After reconstitution, Semaglutide should be stored in a refrigerator at 2-8°C and used within 30 days. For longer storage of reconstituted peptide (up to 6 months), it is recommended to aliquot the solution into individual doses and store at -20°C. However, repeated freeze-thaw cycles should be avoided, as they can degrade the peptide over time. Always check the product’s expiration date and Certificate of Analysis (COA) for specific storage recommendations. At Hanpro Peptides, all our products are shipped with cold packs to maintain stability during transit, and each vial comes with a detailed COA specifying the manufacture date, expiration date, and purity level. It is important to note that Semaglutide should not be stored at room temperature for extended periods, as this can lead to degradation of the peptide and reduced efficacy. The reconstituted solution should be inspected regularly for any signs of degradation, including discoloration, cloudiness, or particle formation. If any of these signs are observed, the solution should be discarded and not used for research purposes.
Related Products for Research
For researchers investigating metabolic health, diabetes, obesity, and related conditions, we recommend exploring these related peptides:
- Tirzepatide – A dual GLP-1 and GIP receptor agonist, known for its potent effects on blood glucose control and weight loss. Often compared to Semaglutide in head-to-head clinical trials, with potentially greater efficacy at higher doses.
- Retatrutide – A triple GLP-1, GIP, and glucagon receptor agonist, currently in clinical development for the treatment of obesity and type 2 diabetes. Early clinical trials have shown unprecedented weight loss efficacy, with mean reductions of up to 24% from baseline.
- Liraglutide – A once-daily GLP-1 receptor agonist, known for its effects on blood glucose control and weight loss. Often used as a first-line GLP-1 receptor agonist in clinical practice and research.
- Dulaglutide – A once-weekly GLP-1 receptor agonist, known for its cardiovascular protective effects and convenient once-weekly dosing. Often used in patients with type 2 diabetes and cardiovascular disease.
- Exenatide – A GLP-1 receptor agonist derived from the saliva of the Gila monster, available in both twice-daily and once-weekly formulations. One of the first GLP-1 receptor agonists to be approved for clinical use.
- Tesofensine – A triple reuptake inhibitor (serotonin, norepinephrine, and dopamine) with appetite-suppressing effects, investigated for the treatment of obesity. Often studied in combination with GLP-1 receptor agonists for enhanced weight loss.
- Ipamorelin – A growth hormone secretagogue that stimulates the release of growth hormone, supporting muscle growth, fat loss, and recovery. Often studied in combination with Semaglutide for synergistic effects on body composition.
- CJC-1295 Without DAC – A growth hormone-releasing hormone (GHRH) analog that increases growth hormone and IGF-1 levels, supporting muscle growth, fat loss, and recovery. Frequently studied in combination with Ipamorelin and other peptides.
Quality Assurance at Hanpro Peptides
At Hanpro Peptides, we are committed to providing researchers with the highest quality peptides available. Our Semaglutide is manufactured in state-of-the-art facilities using solid-phase peptide synthesis (SPPS) technology, ensuring consistent quality and purity batch after batch. The fatty acid side chain and PEG linker are carefully attached during the synthesis process to ensure proper conjugation and biological activity.
Our Quality Control Process Includes:
- High-Performance Liquid Chromatography (HPLC): Every batch is analyzed by HPLC to verify purity ≥99%. This ensures that our products are free from impurities and contaminants that could affect research results.
- Mass Spectrometry (MS): Mass spectrometry is used to confirm the molecular weight and identity of each peptide, ensuring that the product matches the expected amino acid sequence and modifications.
- Certificate of Analysis (COA): Every product comes with a detailed COA that includes the batch number, manufacture date, expiration date, purity level, and test results. Researchers can use this information to verify product quality and document their research materials.
- Microbiological Testing: Our products undergo rigorous microbiological testing to ensure they are free from bacteria, fungi, and other microorganisms.
- Endotoxin Testing: For peptides intended for in vivo studies, we conduct endotoxin testing to ensure that levels are within acceptable limits for research use.
We also offer custom peptide synthesis services for researchers who require specific sequences, modifications, or formulations. Our team of experienced chemists can synthesize peptides ranging from simple dipeptides to complex 50+ amino acid sequences with various modifications, including acetylation, amidation, phosphorylation, fatty acid conjugation, PEGylation, and fluorescent labeling.
Disclaimer
Important Notice: All products sold by Hanpro Peptides are intended for laboratory research purposes only. They are not intended for human consumption, diagnostic use, or therapeutic application. Semaglutide is an FDA-approved prescription medication for the treatment of type 2 diabetes and obesity, but it should only be used under the supervision of a qualified healthcare provider for clinical purposes. Our research-grade Semaglutide is not intended for clinical use or human consumption.
Researchers are responsible for ensuring that their use of our products complies with all applicable local, state, and federal regulations, as well as institutional guidelines and ethical protocols. Our products should only be used by qualified researchers in properly equipped laboratory settings. Animal research should be conducted in accordance with institutional animal care and use committee (IACUC) guidelines, and human subjects research should be conducted in accordance with institutional review board (IRB) guidelines.
The information provided in this product description is for educational and informational purposes only and is based on published scientific literature. It does not constitute medical advice, and we make no claims regarding the therapeutic effects or safety of our products for human use. Any references to potential therapeutic applications are based on preclinical and clinical research and are not intended to suggest that these products are safe or effective for human consumption.
By purchasing and using our products, you acknowledge and agree that you are a qualified researcher, that you will use our products only for legitimate scientific research, and that you assume all responsibility for ensuring compliance with applicable regulations and ethical guidelines.
If you have any questions about our products, quality control processes, or custom synthesis services, please contact our customer support team. We are committed to providing researchers with the highest quality products and exceptional customer service to support your important research endeavors.
| Specification | 5mg*10vials, 10mg*10vials, 15mg*10vials, 20mg*10vials, 30mg*10vials |
|---|
Only logged in customers who have purchased this product may leave a review.
Related products





Reviews
There are no reviews yet.